

Premium File
180 Q&A
$76.99$69.99
HIPAA HIO-201 Exam Questions & Answers, Accurate & Verified By IT Experts
Instant Download, Free Fast Updates, 99.6% Pass Rate
180 Questions & Answers
Last Update: Sep 05, 2026
$69.99
HIPAA HIO-201 Exam Screenshots
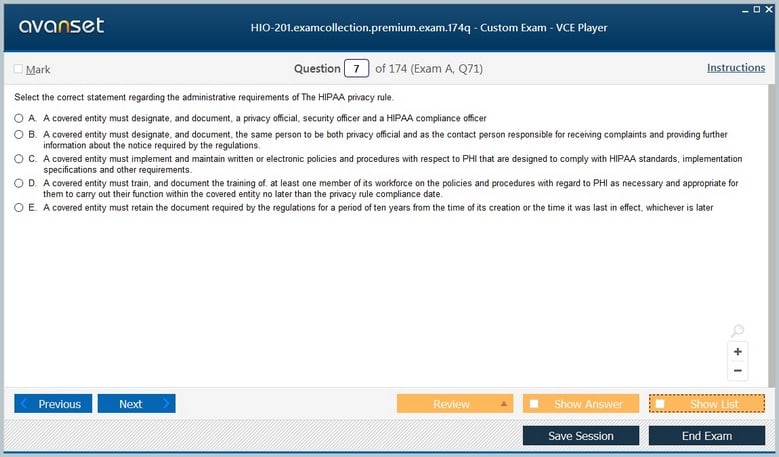
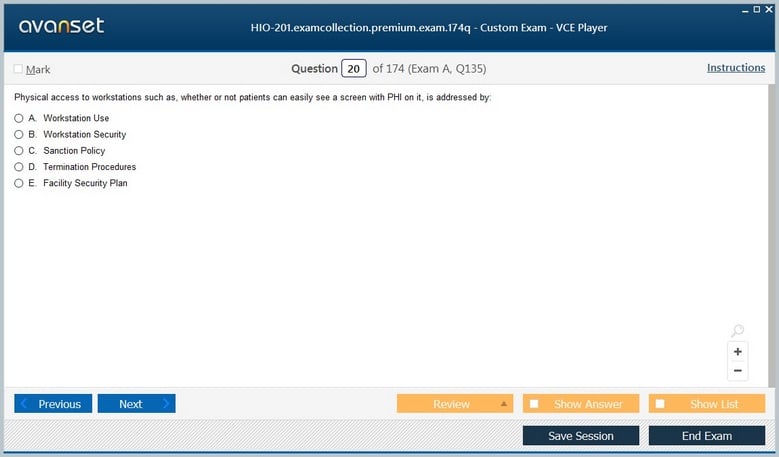
HIPAA HIO-201 Practice Test Questions in VCE Format
| File | Votes | Size | Date |
|---|---|---|---|
File HIPAA.vceplayer.HIO-201.v2026-06-02.by.hudson.108q.vce |
Votes 1 |
Size 134.67 KB |
Date Jun 02, 2026 |
HIPAA HIO-201 Practice Test Questions, Exam Dumps
HIPAA HIO-201 (Certified HIPAA Professional (CHP)) exam dumps vce, practice test questions, study guide & video training course to study and pass quickly and easily. HIPAA HIO-201 Certified HIPAA Professional (CHP) exam dumps & practice test questions and answers. You need avanset vce exam simulator in order to study the HIPAA HIO-201 certification exam dumps & HIPAA HIO-201 practice test questions in vce format.
HIO-201 is ecfirst’s Certified HIPAA Professional (CHP) exam. The credential is current in 2026 and is delivered online. ecfirst publishes a 60-minute format with 60 questions and a 75% passing score. Its stated knowledge areas include HIPAA Administrative Simplification, Transactions and Code Sets, Privacy requirements, and Security requirements, making it a broad private-sector HIPAA education credential rather than a narrow privacy-only assessment.
One distinction should be clear before any study begins: passing HIO-201 does not make an organization “HIPAA certified” by the U.S. Department of Health and Human Services. HHS explicitly states that it does not endorse or recognize private organizations’ certifications regarding the HIPAA Security Rule, and an external certification does not relieve a covered entity of its legal obligations. The CHP credential can validate an individual’s training, but compliance remains an ongoing organizational responsibility.
That distinction improves preparation because it shifts attention from collecting a certificate to understanding how the rules work in practice. A useful HIO-201 study plan asks which entity is regulated, what information is protected, which rule applies, what safeguards are required, how rights and disclosures are handled, how incidents are assessed, and what documentation demonstrates a defensible compliance process.
HIPAA Administrative Simplification includes several interconnected areas. Privacy rules govern uses and disclosures of protected health information and individual rights. Security requirements address safeguards for electronic protected health information. Transactions, code sets, and identifiers support standardized electronic healthcare administration. Breach-notification obligations address certain impermissible uses or disclosures. A candidate should understand where these areas overlap and where they remain distinct.
This matters because “HIPAA” is often used as shorthand for privacy alone. In reality, an organization may have strong confidentiality practices and still have weaknesses in risk analysis, access management, contingency planning, transaction standards, business-associate oversight, or documentation. HIO-201 preparation should use the full regulatory framework rather than reducing every scenario to whether someone was allowed to see a medical record.
The HIPAA credentials inventory provides the natural internal vendor context, while the HIPAA training discussion can deepen the career and education angle. Neither changes the legal standard; they help organize study around the professional knowledge a healthcare privacy or security practitioner needs.
A foundational question in any scenario is who the actors are. HIPAA applies to covered entities such as certain healthcare providers, health plans, and healthcare clearinghouses, and it also imposes direct obligations on business associates that handle protected information on behalf of covered entities. Subcontractors can enter the chain as well. The contractual relationship does not erase regulatory responsibility.
Business associate agreements define permitted uses, safeguards, reporting duties, subcontractor expectations, return or destruction of information, and other responsibilities. Candidates should understand that signing an agreement is not the end of vendor risk management. Organizations still need due diligence, appropriate oversight, incident coordination, and clarity about where data is processed and stored.
Not every organization touching health-related information is automatically a HIPAA covered entity. Consumer health apps, employers, life insurers, schools, and other organizations can fall under different legal frameworks depending on the context. Good exam reasoning starts by identifying the entity relationship before applying a HIPAA requirement.
The Privacy Rule permits certain uses and disclosures without an authorization, including common treatment, payment, and healthcare-operations activities, while other purposes may require authorization or fall under specific exceptions. Candidates need to distinguish authorization from consent language used informally and recognize that different disclosure situations can have different conditions.
The minimum-necessary concept is another frequent source of confusion. It generally requires reasonable efforts to limit certain uses, disclosures, and requests to the information needed for the purpose, but it is not a universal rule applied identically to every disclosure. Study should focus on when the principle applies, how role-based access supports it, and why clinical treatment workflows have different considerations.
Individual rights include access to records, requests for amendment, accounting in applicable circumstances, restrictions, confidential communications, and notice of privacy practices. The operational challenge is converting those legal rights into repeatable workflows with identity verification, deadlines, documentation, and escalation paths. Privacy compliance succeeds through processes, not just policy statements.
The Security Rule organizes safeguards into administrative, physical, and technical areas. Administrative safeguards address governance, risk analysis, workforce security, incident procedures, contingency planning, and related management processes. Physical safeguards address facility and device concerns. Technical safeguards address access controls, audit controls, integrity, authentication, and transmission security.
The rule’s risk-based design means candidates should avoid searching for one mandatory product list. Encryption, multifactor authentication, endpoint controls, backups, logging, segmentation, and other technologies can be important safeguards, but compliance depends on the organization’s risks, environment, documentation, and reasonable implementation choices. A control is meaningful when it addresses a known risk and is operated effectively.
Risk analysis is especially important because it connects the rule to the actual environment. Organizations need to identify where electronic protected health information exists, relevant threats and vulnerabilities, existing safeguards, likelihood and impact, and residual risk. An inventory that ignores cloud platforms, mobile devices, interfaces, backups, vendors, or shadow systems produces a weak foundation for the rest of the security program.
Finding a vulnerability is not the same as managing risk. A remediation program needs ownership, priorities, due dates, resources, compensating controls, acceptance criteria, and evidence of completion. High-risk issues should not disappear into a spreadsheet simply because the organization performed an annual assessment.
Risk decisions also need context. A legacy clinical device may be difficult to patch because of vendor support or patient-safety constraints. The organization still needs to address the risk through segmentation, access restrictions, monitoring, replacement planning, or other measures. The existence of an operational constraint does not remove the need to understand and manage exposure.
Periodic evaluation matters because environments change. Acquisitions, new cloud services, telehealth, remote work, ransomware threats, system upgrades, new business associates, and regulatory changes can alter risk. Compliance should therefore be treated as a lifecycle of assessment, remediation, monitoring, and reassessment rather than as a one-time project before an audit.
Administrative Simplification also standardizes electronic healthcare transactions so organizations do not need a unique data exchange method for every payer or trading partner. Claims, eligibility, claim status, remittance, enrollment, premium payments, and related transactions use defined standards and code sets. Candidates do not need to become claims programmers, but they should understand why standardization exists and how it supports efficient exchange.
Identifiers such as the National Provider Identifier support consistent identification across transactions. Code sets such as ICD and procedure-related coding standards represent clinical or administrative information within defined contexts. Errors can lead to rejected transactions, payment delays, inaccurate reporting, or downstream data-quality problems.
Security and privacy still apply when standardized transactions are used. A transaction can be technically valid and still be sent to the wrong recipient, contain more information than appropriate, or be exposed through weak controls. Standards improve interoperability; they do not replace confidentiality, integrity, authentication, or access-management responsibilities.
When protected information may have been exposed, the first task is to understand what happened: what data was involved, who accessed or received it, whether it was actually acquired or viewed, what protections were in place, and what mitigation occurred. Organizations need an incident process that preserves evidence, limits further exposure, coordinates legal and operational teams, and documents decisions.
Not every security incident is automatically a reportable breach, and candidates should avoid collapsing those terms. Breach analysis depends on the regulatory definitions and the facts of the event. Documentation is critical because an organization may need to show how it reached its conclusion and what mitigation it performed.
Ransomware illustrates the overlap between security and privacy. The immediate problem may be availability, but encrypted or exfiltrated data can create confidentiality concerns as well. Contingency planning, offline or protected backups, incident communications, access controls, monitoring, and recovery procedures all influence the organization’s resilience.
Policies only work when workforce members understand their responsibilities and systems support the expected behavior. Training should be appropriate to roles, refreshed when risks or procedures change, and reinforced by sanctions, access controls, reporting channels, and management behavior. A once-a-year slide deck is not a complete workforce security program.
Governance establishes responsibility. Privacy, security, compliance, legal, IT, clinical operations, HR, procurement, and executive leadership can all have roles. Clear ownership prevents gaps where everyone assumes another team is responsible for a safeguard or incident decision. Smaller organizations may combine roles, but the responsibilities still need to be performed.
Documentation should reflect reality. A policy that says access is reviewed quarterly provides little protection if no review occurs. Auditors and regulators can ask for evidence of risk analyses, training, business-associate management, incident response, contingency tests, access reviews, and remediation. Operational proof matters.
ecfirst currently markets the CHP exam as an online credential covering Privacy, Security, Transactions and Code Sets, and Administrative Simplification. Its current 60-question, 60-minute, 75%-passing format gives candidates a clear assessment target. The program can be useful for professionals who need structured HIPAA education across those domains.
But the most important exam-day fact may also be the most important career fact: the credential belongs to ecfirst, not HHS. HHS says private Security Rule certifications are not endorsed or recognized as a substitute for legal obligations. A professional should be able to explain that distinction accurately to employers and clients instead of promising that one exam can “certify HIPAA compliance.”
For broader digital-health professionals, CAHIMS covers a wider health-information-systems foundation, while HIO-201 goes deeper into HIPAA-specific regulatory knowledge. The two can complement each other, but they validate different bodies of knowledge. The strongest HIO-201 preparation combines regulatory reading, realistic scenarios, and a clear understanding of how privacy and security controls operate inside real healthcare processes.
Go to testing centre with ease on our mind when you use HIPAA HIO-201 vce exam dumps, practice test questions and answers. HIPAA HIO-201 Certified HIPAA Professional (CHP) certification practice test questions and answers, study guide, exam dumps and video training course in vce format to help you study with ease. Prepare with confidence and study using HIPAA HIO-201 exam dumps & practice test questions and answers vce from ExamCollection.
Purchase Individually
Site Search:

SPECIAL OFFER: GET 10% OFF

Pass your Exam with ExamCollection's PREMIUM files!
SPECIAL OFFER: GET 10% OFF
Use Discount Code:
MIN10OFF
A confirmation link was sent to your e-mail.
Please check your mailbox for a message from support@examcollection.com and follow the directions.

Download Free Demo of VCE Exam Simulator
Experience Avanset VCE Exam Simulator for yourself.
Simply submit your e-mail address below to get started with our interactive software demo of your free trial.